• Skip to primary navigation
  • Skip to main content
  • Skip to primary sidebar
  • Skip to footer
Raleigh Gynecology & Wellness, PA Site Logo

Raleigh Gynecology & Wellness

North Carolina GYN Care & Treatment

  • (919) 525-3959
  • Schedule Appointment
  • About
    • Contact
    • Our Team
  • Patient Forms
  • Routine Care
    • Breast Care
    • Contraceptive Care
    • Emergency Contraception
    • Gardasil Vaccination
    • GYN Wellness Screening
    • HPV Counseling
    • PAP Test
    • STD Testing
    • Mammography
  • Conditions & Management
    • Abnormal PAP Smears
    • Endometriosis
    • Initial Evaluation of Infertility
    • Menopause & Peri-Menopause Care
    • Menstrual Disorders
    • PCOS
    • Pelvic Relaxation & Prolapse
    • Sexual Health & Sexual Dysfunction
    • Urinary Problems
    • Vaginal Dryness & Painful Sex
    • Vaginitis Care
  • Procedures
    • Colposcopy
    • Endometrial Biopsy
    • IUD Insertion
    • LEEP
    • Nexplanon
    • Nitrous Oxide
    • Pessary Fitting
    • Sonohysterography & Ultrasound
  • Patient Portal

A Guide to Metabolism and Weight Changes in Perimenopause

Conditions and Management

Raleigh Gynecology November 16, 2026

mature woman holding paper with word MENOPAUSE and weight scales on light backgroundWomen may notice their bodies changing in their 40s, even when eating and exercise habits stay the same, and perimenopause is often part of the reason. Research following women through the menopause transition links it to faster fat gain and declining lean mass, and shifting hormones make weight around the belly more likely. The scale can hide these shifts, because total weight climbs while the balance of fat and lean mass shifts underneath it.

Lifespan data on calorie burn does not point to a sudden metabolic crash in the 40s, though sleep, genetics, activity levels, and natural aging are all involved. Realistic habits, such as strength training and better sleep, support health through this stage, and persistent changes should prompt a visit to a gynecologist.

When Perimenopause Begins and How Long It Lasts

Perimenopause usually begins in a woman’s mid- to late 40s and lasts about four years on average, according to the U.S. Department of Health and Human Services (HHS) Office on Women’s Health. The range spans two to eight years. Hormone levels rise and fall unpredictably during this time, which is why periods become irregular and hot flashes or poor sleep can appear.

How Perimenopause Alters Body Fat and Muscle Mass

Research from the Kaiser Permanente Division of Research, which summarized findings from the federally funded Study of Women’s Health Across the Nation, found that women experienced twice the rate of fat accumulation once the menopause transition started, while lean mass began to decrease. Both changes persisted for approximately two years following the last period before stabilizing.

Weight on the scale rose, without a jump at the start of the transition, because fat gains accompanied lean mass losses. The number alone can therefore understate what is changing.

The Mayo Clinic notes that the hormonal changes of menopause tend to make weight gain around the belly more likely than around the hips and thighs. Carrying excess fat in the abdominal area increases the chance of developing type 2 diabetes and cardiovascular disease.

What Research Shows About Metabolism in Your 40s

aged women on a weight scale

A 2021 study in Science measured daily calorie burn in more than 6,600 people spanning infancy through age 95 across 29 countries. According to the Duke University Population Research Institute’s summary of the study, energy expenditure was most stable in the 20s, 30s, 40s, and 50s, and metabolism began a gradual decline of 0.7% per year only after age 60.

The Duke summary suggests that a changing metabolism does not explain the thickening waistlines common in midlife. The Mayo Clinic attributes this at least in part to muscle loss, noting that as people age, muscle mass generally decreases while fat tends to increase, and that less muscle causes the body to burn calories more slowly. Eating the way you always have without moving more is likely to lead to weight gain.

Other Factors Behind Midlife Weight Gain

Trouble sleeping is a recognized perimenopause symptom, and the Mayo Clinic notes that people who sleep too little tend to eat more and move less. Genetics also contribute, since women whose close relatives carry extra weight around the abdomen are more likely to do the same. The Mayo Clinic describes weight gain continuing at about 1.5 pounds per year through the 50s.

Habits That Support Health During Perimenopause

Guidance from HHS and Mayo Clinic supports three habits.

  • Moderate aerobic activity, such as brisk walking, for 150 to 300 minutes each week, is the adult target in the HHS Physical Activity Guidelines for Americans.
  • Resistance-based exercises, like weightlifting or push-ups, should be performed on a minimum of two days per week. Mayo Clinic notes that strength training also helps maintain bone density, which decreases with menopause.
  • Protect your sleep, since Mayo Clinic notes that moving more may help women sleep better, and that better sleep can make exercise easier.

Symptoms to Bring Up at Your Next Visit

Weight changes alongside irregular periods, hot flashes, or disrupted sleep are worth raising with a gynecologist. Tracking your periods and symptoms helps, because the HHS Office on Women’s Health notes that hormone levels shift unpredictably during the transition and blood hormone tests are not usually recommended without a medical reason.

Menopause and perimenopause care can include changes in diet and exercise as well as relaxation techniques. In some cases, prescription medication can help, including hormone therapy and non-hormonal options. The Mayo Clinic notes that hormone therapy may help redistribute fat that accumulates around the belly. However, that redistribution has not been tied to weight loss.

Annual GYN wellness screening visits also cover nutrition and exercise, along with breast and cervical cancer screening, and mammograms are recommended beginning at age 40. Pregnancy is still possible during perimenopause, even after a skipped period, and the HHS Office on Women’s Health advises continuing birth control until a full year has passed since the last period, so contraceptive care belongs in the same conversation.

Schedule a Perimenopause Visit with Raleigh Gynecology & Wellness

doctor planning a weight loss plan

At Raleigh Gynecology & Wellness, our all-women team has cared for women for over 30 years, guiding each visit with evidence-based medicine and attention to the mind-body connection. We begin by taking the time to understand both your symptoms and your goals, and then we create a plan that addresses each of them.

To talk through weight changes or other symptoms, schedule an appointment online for perimenopause care in Raleigh or call (919) 636-6670.

Raleigh Gynecology October 30, 2026

stressed old woman waving fan suffer from overheating at homeWomen in their 40s and 50s may expect a few menopause symptoms, such as hot flashes, uneven cycles, and nights of broken sleep. Knowing which changes to bring to a gynecologist is less obvious.

Six signs warrant a menopause evaluation, and each has a clear point for booking a visit.

You Can Judge a Menopause Change by Its Pattern and Daily Impact

In medical terms, you reach menopause once a full year has passed since your last period. Perimenopause is the name for the stretch before that. Changes can start during this time, even while your cycles are still regular, and it is easy to mistake them for stress, a busy job, or getting older.

You can usually spot abnormal menopause symptoms in two ways. The first is a clear change in pattern, such as bleeding after a year without a period. The second is the effect on your day, for instance being unable to sleep through the night, work a full day, or have comfortable sex.

Six Menopause Symptoms to Bring to Your Gynecologist

Bleeding Returns After a Year Without Periods

Call your gynecologist about any spotting or blood you notice after a full year without periods, even if it happens only once. In April 2026, the American College of Obstetricians and Gynecologists (ACOG) issued updated guidance. The group reported that about 9 in 10 patients diagnosed with cancer of the uterine lining had bleeding after menopause.

For most people in this situation, ACOG now advises two initial tests, a transvaginal ultrasound and an endometrial biopsy. During that procedure, a provider takes a small sample of tissue from inside the uterus. The group changed its advice after researchers found that some cancers were missed when ultrasound was the only test.

Before your periods stop, you may skip some or notice a lighter or heavier flow. ACOG draws clearer lines in its guidance on abnormal cycles. Book a visit if you need a fresh pad or tampon every hour, bleed for more than seven days, or start a new period fewer than 21 days after the last one began.

Spotting after sex, or in the middle of your cycle, is also a reason to call. If you feel dizzy or faint during heavy bleeding, and if you are changing pads or tampons hourly for more than four hours, go to an emergency room right away.

You Lose Sleep to Hot Flashes and Night Sweats

If you wake from hot flashes several nights a week, change soaked sheets, or struggle through meetings or workouts, book a visit. Without treatment, they can last much longer than a few months.

In a 2015 analysis of data from the Study of Women’s Health Across the Nation (SWAN), the median length of frequent hot flashes and night sweats was 7.4 years. Women who experienced symptoms early in the transition had them longer. ACOG lists hormone therapy as one treatment for these episodes.

A provider will weigh the benefits of treatment versus the risks based on your own health history and your family’s before recommending hormone therapy. This review is a standard step in menopause care before any menopause treatment begins.

Low Mood or Anxiety Lasts for Weeks

Short bursts of irritability are common perimenopause symptoms. Tell your gynecologist if you feel sad or anxious most days for several weeks, if you no longer look forward to hobbies you used to enjoy, or if you have sudden panic attacks.

middle-aged woman sitting at home holds her hands on her temples. Headache, women's health, hormonal levelsThe North American Menopause Society, now The Menopause Society, published depression guidelines in 2018 describing perimenopause as a stage of higher risk for depression, including for anyone who has never had it. The same panel also found that women with a past major episode are more likely to have another during these years.

Because mood changes, night waking, and hot flashes can affect each other, a gynecologist may look at them together. If you have thoughts of harming yourself, call or text the 988 Lifeline right away, or call 911.

Vaginal Dryness or Painful Sex Gets Worse Over Time

Doctors group vaginal dryness, irritation, and pain with sex under one diagnosis called genitourinary syndrome of menopause (GSM). In its 2020 position statement, The Menopause Society describes it as a long-term condition that tends to worsen unless it is treated.

Unlike hot flashes, these changes may not resolve on their own, and mild discomfort can get harder to live with. Pain with sex can also feel too private to mention or easy to dismiss as part of midlife. It is a treatable medical symptom to speak about with your gynecologist.

Schedule an evaluation if you have stopped having sex because of pain. The same goes for burning or spotting from dryness during everyday activities, or discomfort that has gotten worse over several months.

You Have Repeated Urinary Infections

GSM can involve the urethra and bladder too, and some women notice more leaking or urgency in midlife as a result. In its 2025 guideline, the American Urological Association defines recurrent urinary tract infections (UTIs) as two separate infections within six months during the past year.

If that definition fits your history, see a gynecologist. Book a visit, too, if burning returns after treatment or you have started leaking urine during daily activities. If you also have a fever, chills, or pain in your side or back, get care the same day. Those signs may be associated with a kidney infection.

Joint Pain or Memory Changes Have No Clear Explanation

About two-thirds of women in SWAN reported forgetfulness or similar complaints during the menopause transition. On formal tests, participants showed a temporary dip in processing speed and verbal memory that went away after their periods stopped.

Forgetfulness that keeps getting worse is outside that pattern, and so is trouble managing familiar tasks. Both are worth an evaluation, as is anything family members point out.

Midlife joint pain can come from hormone changes, arthritis, or an old injury. Bring up swelling, redness, warmth, or stiffness that makes it hard to move. Your gynecologist can help sort out whether menopause, another condition, or both are involved, and whether you need a specialist.

A Written Symptom Record Makes the First Visit More Productive

With written notes, a provider can see patterns that are hard to describe from memory during a menopause evaluation. Track three things: timing, severity, and impact.

Timing means the first day of each period or episode of spotting, how long bleeding lasts, and when hot flashes or night waking happen. A provider can learn far more from two or three months of calendar entries than from a single week.

Severity means rating each symptom from 1 to 10, counting the pads or tampons you use on your heaviest days, and noting how many times you wake each night. Exact numbers matter less than consistency, since a provider is looking for changes over time.

Impact means the daily activities you skip or struggle with because of a symptom, such as finishing a workday, exercising, or having sex comfortably. Add a list of your medications and supplements. The right next step depends on that full picture of your menopause health, and an appointment is where you and your gynecologist work it out.

Schedule a Menopause Evaluation with Our All-Women Team

woman suffering from headache, touching temples, menopause lying in bed at home

Bring your notes to a menopause doctor, even if you have tracked only one of these signs. Raleigh Gynecology & Wellness has focused on women’s health for more than 30 years.

Our all-women team can go over what you recorded and adjust your care at follow-up visits. You can book a menopause visit online or call 919-636-6670.

Raleigh Gynecology October 23, 2026

doctor showing medical information, scan results on tablet to patientA 25-year-old and a 45-year-old need very different things from women’s preventive health, and the list keeps changing after that.
This guide covers the exams and screenings behind a full plan, plus the age, family history, and other factors that move the timeline for each.

One Well-Woman Visit a Year Anchors the Screening Schedule

Nearly everything in preventive women’s healthcare circles back to a single appointment, the well-woman exam. It’s where other screenings get scheduled, reviewed, or adjusted. Federal guidelines set the frequency at once a year, though a patient and provider can split the recommended services across two sittings if a single visit runs short on time.

That flexibility matters because certain subjects are hard to bring up right away. Painful sex, urine that leaks during a laugh or a sneeze, and a partner’s infection are not easy to raise on the spot, and a second appointment gives a patient room to talk about them without feeling rushed.

Come prepared for your next women’s health checkup with the date of your last Pap test, your vaccine records, and a few notes on your recent cycles. Those details give your provider somewhere to start when it comes time for a GYN wellness screening.

Cervical Cancer Screening Intervals Shift as Women Age

Ages 21 to 29 get a Pap test every three years. Once a patient turns 30, the guidance changes. The American College of Obstetricians and Gynecologists, known as ACOG, now favors testing every five years for cancer-linked strains of the human papillomavirus, or HPV,as the primary method, though cytology alone every three years and cotesting every five year remain an acceptable choices.

A January 2026 update to the federal Women’s Preventive Services Guidelines added another path for patients at average risk, ages 30 to 65, who can choose a self-collected sample. ACOG folded that choice into its own recommendations in July 2026. However, the patient collected sampling option should only be offered if patients prefer this option and if there is appropriate oversight for collection, notification, documentation and referral for followup as indicated.

Screening can stop after 65 only when a patient’s prior results were both normal and adequate, and a provider may ask about those older results to confirm it. An abnormal history changes the plan. From there, a patient follows her own separate follow-up schedule, set by her provider.

Breast Cancer Screening Guidance Differs Between the Task Force and the American Cancer Society

The U.S. Preventive Services Task Force put the standard at every two years in its 2024 statement, covering women 40 to 74 who carry an average risk profile.

The American Cancer Society lands somewhere else entirely, recommending annual mammograms from 45 to 54 and the choice to begin at 40. Once a woman turns 55, the ACS notes that every other year is acceptable.

Two different guidelines mean a patient in her early 40s isn’t locked into a single path. She has a few reasonable options worth raising with her provider. Family history changes that choice further. A breast care visit is the place to weigh personal risk, prior mammogram results, and preference together.

HPV Vaccination and STD Testing Follow Separate Age-Based Schedules

The Centers for Disease Control and Prevention, or CDC, sets age 11 or 12 as the standard start for HPV vaccination. Anyone who missed that window still has catch-up doses available through age 26.

concept of preventive health care and vaccination for teenagersAdults 27 to 45 aren’t excluded either. They can still ask a provider whether the vaccine makes sense at that point. Most people in that range have already been exposed to some of the virus types it targets, so the added benefit is smaller.

STD testing follows its own set of intervals. Sexually active women under 25 should plan on yearly chlamydia and gonorrhea screening, per CDC guidance.

The same interval applies to older patients with a new partner, multiple partners, or a partner with a known infection. HIV testing casts an even wider net. Everyone from 13 to 64 should get tested at least once, whatever their individual risk factors look like.

A routine appointment is also the easiest place to mention sexual history, since that’s what keeps both STD screening and a Gardasil vaccination schedule on track.

Age, Family History, and Existing Conditions Shift the Screening Timeline

Three factors shift women’s health screenings away from a standard chart: age, family history, and existing conditions.

Age determines when cervical screening can stop, as described above, and when bone density testing should begin. The Task Force updated its standards in 2025, setting a dual-energy X-ray absorptiometry (DXA) scan at 65 for every woman and moving that timeline earlier for postmenopausal women whose fracture risk comes back elevated on a clinical assessment tool.

Family history shifts things too, especially when breast, ovarian, tubal, or peritoneal cancer runs in close relatives. A short questionnaire, recommended by the U.S. Preventive Services Task Force, flags an elevated BRCA mutation risk, and anyone who screens positive should receive genetic counseling and testing. Jot down which relatives were affected and their age at diagnosis before that visit.

Existing conditions add a layer few generic checklists cover. ACOG connects polycystic ovary syndrome, or PCOS, to higher long-term odds of type 2 diabetes, cardiovascular disease, and endometrial cancer, most of it driven by insulin resistance and by ovulation that turns irregular or stops for long stretches.

Endometriosis needs its own tracking of cycle length, pain levels, and bleeding patterns, which is information a provider uses to manage the condition over time.

Perimenopause and Menopause Add New Considerations to the Plan

For most women, the menopausal transition starts somewhere between 45 and 55, though the National Institute on Aging notes that menopause itself is not official until 12 consecutive months have passed without a menstrual cycle.

Along the way, periods that arrive very close together, heavy bleeding, spotting between periods or after sex, one lasting more than a week, and any bleeding after a full year without one are all reasons to call a provider. If dizziness or severe pain shows up too, it’s time for emergency care right away.

Contraception needs shift during this stretch, too. Pregnancy remains possible until a full year has passed since the last period. Bone health and heart health also move to the front of the conversation once that milestone arrives, alongside the hot flashes and sleep changes patients tend to ask about first.

Menopause and perimenopause care brings those threads together in one visit.

Staying with One Gynecology Team Keeps Screening Records Accurate

asian female doctor using a stethoscope to examine a patientA five-year HPV screening interval depends on an accurate record of the last test’s date and result. Vaccine doses need that same kind of tracking, and a mammogram’s timing relies on comparing it against the one before.
Many women start searching for OB-GYN care right after a screening comes due, and that paper trail is the practical reason to build a plan with a single gynecology team instead of restarting the conversation with a new office each time.

Bring Your History to Your Next Appointment

Raleigh Gynecology & Wellness has provided preventive care for women in Raleigh for more than 30 years, and our all-women team can review your Pap history, vaccine records, and family history to map out what comes next for you specifically.

Schedule your appointment online and bring your questions with you.

Raleigh Gynecology May 4, 2026

Essential Takeaways:

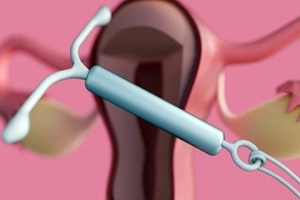
  • 3D rendering of a cross-sectional view of the female reproductive system featuring an Intrauterine Device or IUDMild cramping, spotting, and period changes are common in the first few months after IUD placement.

  • Hormonal and copper IUDs can cause different side effects, especially when it comes to bleeding patterns.
  • Most IUD-related symptoms improve as your body adjusts over time.
  • Severe pain, heavy bleeding, fever, or unusual discharge should be evaluated promptly.
  • Open communication with your women’s health provider can help you feel informed and confident in your birth control choice.

What You Might Experience After IUD Placement

You chose an IUD because you wanted reliable, low-maintenance birth control. It is one of the most effective options available, and for many women it offers years of protection without daily effort. However, after placement, you may notice changes in your body that leave you wondering, “Is this normal?”

It’s common to feel uncertain about what changes to expect after IUD placement. Friends may share stories that do not match your experience, and online forums can increase anxiety instead of offering reassurance. The truth is that most IUD side effects are temporary and manageable. Let’s review some common side effects that often catch women off guard.

1. Cramping That Lasts Longer Than You Expected

Many women expect cramping on the day of insertion, but you might be surprised if it continues for several days or even a few weeks. Mild to moderate cramping is common as your uterus gradually adjusts to the IUD.

Your uterus is a muscle, and it may contract as it adapts to the IUD. For most women, this improves within three to six months. Using over‑the‑counter pain relievers, applying heat, and resting can help reduce symptoms.

If you have severe pain that doesn’t improve, or pain accompanied by fever, call your provider. While rare, complications such as infection or IUD displacement need prompt evaluation.

2. Spotting Between Periods

Unexpected spotting can be frustrating, especially if you chose an IUD for convenience. Light bleeding between periods is a common early side effect, particularly with hormonal IUDs.

The American College of Obstetricians and Gynecologists (ACOG) notes that irregular bleeding is common in the first few months after hormonal IUD placement, gradually getting better in two to six months.

Copper IUDs, on the other hand, are more likely to cause heavier or longer periods, especially during the first several cycles. Research shows that up to 70% of copper IUD users report increased menstrual bleeding in the early months.

Tracking your cycle and keeping a record of bleeding patterns can help you and your provider determine whether what you are experiencing falls within the expected range.

3. Heavier or Lighter Periods

birth control intrauterine devices

Your period may feel different than what you are used to. With a copper IUD, you might have heavier bleeding and more severe cramps at first and for some women these effects are more persistent. With a hormonal IUD, periods often become lighter and shorter, and in some cases may stop completely.

Up to approximately 20% of women who use a hormonal IUD will stop having periods after one year of use, depending on the IUD brand. This can feel concerning if you are not expecting it, but it is generally safe and related to the thinning of the uterine lining.

If your bleeding becomes extremely heavy, meaning you are soaking through a pad or tampon every hour for several hours, you should contact your provider.

4. Mood Changes or Breast Tenderness

Hormonal IUDs release a small level of progestin in the uterus. While hormone levels in the bloodstream are much lower than with birth control pills and systemic side effects are uncommon, some women do report mood changes, acne, headaches, or breast tenderness.

Not every woman experiences these symptoms, and many notice improvement after the first few months. If mood changes feel significant or affect daily life, don’t ignore them. Open communication with your provider can help determine whether your symptoms are likely related to your IUD or influenced by other factors such as stress or life changes.

5. Feeling the Strings or Partner Discomfort

After placement, your provider will trim the IUD strings so they sit near the cervix. Occasionally, you may feel the strings when checking them, or your partner may notice them during intercourse.

In most cases, the strings soften over time and become less noticeable. If they feel too long or cause discomfort, your provider can adjust them.

It is also important to check your strings periodically, especially in the first few months. Expulsion means the IUD partially or completely comes out. ACOG reports that expulsion occurs in about 2-10% of users. If you cannot feel the strings or think that the IUD may have shifted, schedule an appointment for evaluation.

When Something Is Not Normal

While most side effects are temporary, certain symptoms should prompt you to call your provider. These include:

  • Severe abdominal pain
  • Fever or chills
  • Foul-smelling discharge
  • Very heavy bleeding
  • Signs of pregnancy or a positive pregnancy test

Remember, if something feels off, it is always appropriate to seek medical advice.

Trust Raleigh Gynecology With Your Contraceptive Care

gynecologist holding an IUD birth control device before using it for patient

Choosing an IUD is a personal decision, and your experience should not leave you feeling confused or dismissed. Many side effects are normal and improve with time, but you do not have to manage them alone.

At Raleigh Gynecology & Wellness, we take your concerns seriously. Whether you are considering an IUD, adjusting to a new one, or wondering if your symptoms are typical, we are here to provide thoughtful, individualized care. If you have questions about your IUD or would like to explore your birth control options, schedule an appointment with our team today.

Raleigh Gynecology December 22, 2025

Essential Takeaways:

  • Research confirms that underwire bras are not linked to breast cancer or other serious breast conditions.
  • The comfort and fit of your bra have a greater effect on your well-being than whether it contains an underwire.
  • Normal bra wear, including underwire styles, does not block lymphatic drainage or trap toxins in breast tissue.
  • Factors like genetics, aging, and pregnancy influence breast shape more than the type of bra you wear.
  • Consistent screenings, self-checks, and wearing supportive, comfortable bras are the best ways to care for your breast health.

healthy women wearing underwire braYou probably wear a bra most days without thinking twice. However, stories in the media that claim that underwires could be “bad for your breasts” may raise concerns. Maybe you’ve heard that they block lymph flow, cause chronic pain, or even increase the risk of breast cancer. It’s understandable to wonder if there’s any truth behind these rumors. When it comes to your breast health, it’s natural to want to take all precautions.
So, do underwire bras really affect your breast health? Find out what the research actually says and what matters most for your comfort and long-term well-being.

The Myth: Underwire Bras and Breast Cancer

One of the most common concerns about underwire bras is the effect of the wire against the torso. The wire has been thought to compress lymph nodes, trapping “toxins” and raising the risk of breast cancer. However, there is little scientific evidence to support these claims.

A landmark study from the Fred Hutchinson Cancer Research Center found no link between bra-wearing habits, including the use of underwire bras, and breast cancer risk in postmenopausal women. Researchers examined factors such as hours of daily wear, age at first bra use, and bra type and found no association.

Similarly, Harvard Health Publishing reviewed the data. It concluded that no link was seen between the risk of either invasive ductal carcinoma or lobular carcinoma with regard to bra wearing, including use of an underwire.

The Real Issue: Comfort, Fit, and Support

Even though underwires are not believed to be dangerous, that doesn’t mean every bra is good for you. The real impact of a bra on your body has more to do with fit than with design.

If your bra leaves red marks, digs into your skin, or feels uncomfortable by midday, that’s a sign that something is off. Poorly fitted bras can cause shoulder and neck pain, possible posture issues, and chronic skin irritation. These issues do not just affect women who wear underwire bras but can be worse if the wire presses too tightly against the ribs or breast tissue.

In fact, many women regularly wear the wrong bra size and don’t know it. According to the Chiropractic & Osteopathy journal, around 80% of women are wearing bras that don’t fit correctly. A properly fitted bra should support you without pinching, digging, or slipping.

If you’ve had breast surgery, radiation, or lymph node removal, your healthcare provider might recommend avoiding underwire bras for a while to allow healing. That’s less about the wire itself and more about preventing friction on sensitive tissue.

What About Lymph Flow and Sagging?

You may have heard claims that wearing underwire bras, or any bras, can block lymphatic drainage or make breasts sag faster. Current research does not support these ideas either.

Lymphatic drainage happens through deep channels in the body, not the surface areas where a bra sits. There’s no evidence that typical bra pressure, even from underwires, restricts that flow in healthy women.

As for sagging, it’s influenced by genetics, age, pregnancy, breastfeeding, and gravity, not by whether you wear a bra. A French study from the University of Besancon even suggested that consistent bra use doesn’t prevent sagging and might slightly affect natural ligament tone, although more research is needed.

What You Can Do for Better Breast Health

You don’t need to toss all your underwire bras. Instead, focus on these healthy habits that truly support your breast well-being:

  1. doctor checking woman's breast at hospital, closeupGet fitted regularly. Your body changes over time due to weight shifts, hormones, and aging, all of which can affect breast size and shape. A professional fitting every year or two helps keep your bras supportive and comfortable.
  2. Listen to your body. If your bra feels too tight, causes soreness, or leaves indentations, it’s time to adjust your size or try a different style.
  3. Take breaks when you want to. There’s no medical need to wear a bra all day, every day. If you’re at home and comfortable without one, that’s perfectly fine.
  4. Keep up with screenings. Mammograms, self-awareness, and regular checkups do far more for early detection than any bra choice ever could.
  5. Choose what makes you feel confident. Whether that’s an underwire bra, a soft bralette, or going wire-free entirely, your comfort and confidence are part of good breast health.

Received Specialized Care at Raleigh Gynecology & Wellness

There’s no credible scientific evidence that underwire bras harm your breast health or increase cancer risk. What matters most is wearing bras that fit well, support you comfortably, and make you feel good in your own body.

If you’re experiencing discomfort, noticing changes, or just want professional guidance on maintaining breast health, our women’s health specialists are here for you. Schedule a visit today to review your breast health and get personalized comfort recommendations.

  • Page 1
  • Page 2
  • Page 3
  • Interim pages omitted …
  • Page 21
  • Go to Next Page »

Primary Sidebar

Have A Question?

  • This field is for validation purposes and should be left unchanged.

Footer

Raleigh Gynecology

2304 Wesvill Court,Suite 210Raleigh, NC 27607(919) 636-6670

Link to company Facebook page

Link to company Twitter page

Link to company Instagram page


  • About
  • Blog
  • Contact
  • Patient Forms
  • Anti-Discrimination Policy

Conditions & Management

  • Abnormal PAP Smears
  • Endometriosis
  • Initial Evaluation of Infertility
  • Menopause & Peri-Menopause Care
  • Menstrual Disorders
  • PCOS
  • Pelvic Relaxation & Prolapse
  • Sexual Health & Sexual Dysfunction
  • Urinary Problems
  • Vaginal Dryness & Painful Sex
  • Vaginitis Care

Procedures

  • Colposcopy
  • Endometrial Biopsy
  • IUD Insertion
  • LEEP
  • Nexplanon
  • Pelvic Floor Therapy
  • Pessary Fitting
  • Sonohysterography & Ultrasound

Routine Care

  • Breast Care
  • Contraceptive Care
  • Emergency Contraception
  • Gardasil Vaccination
  • GYN Wellness Screening
  • HPV Counseling
  • Mammography
  • PAP Test
  • STD Testing

© 2026 Raleigh Gynecology & Wellness, PA · Powered by 321 Web Marketing · Website Privacy Policy & Terms of Use

Popup Modal: Online Scheduling Existing Patients Only

Online scheduling is ONLY for existing patients. All new patients must call the office to schedule.